Born Without Lateral Incisors? Fixing Canine Substitution Years After Braces

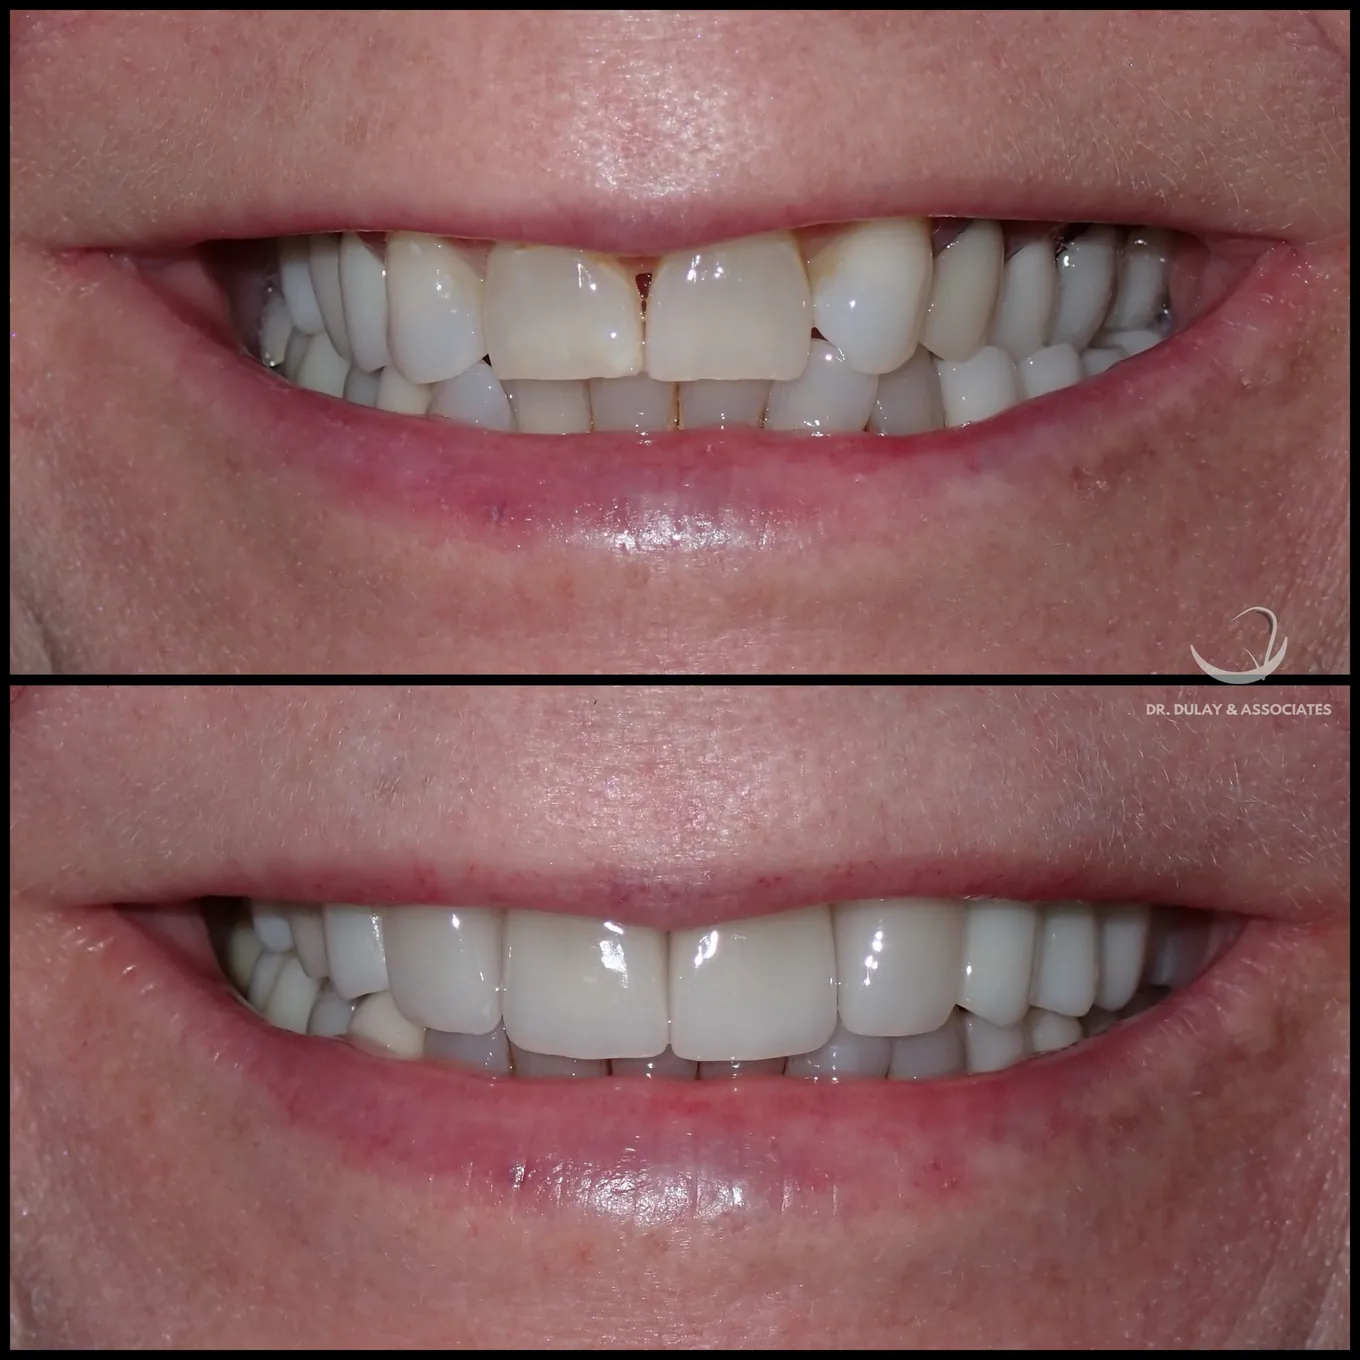
Before and after: short, stained front teeth with wide canines standing in for missing lateral incisors, then longer front teeth with the canines reshaped as laterals.

Above: before (top) and after (bottom). Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

You had braces as a teenager. You were told you were born without two teeth, and the orthodontist closed the gaps. It worked, and for years you didn’t think about it. Now the teeth beside your front teeth look pointed, almost like vampire teeth, and too heavy for where they sit, your front teeth look short, and your smile looks narrower than it should.

That isn’t your imagination, and it isn’t just age. It is what canine substitution looks like decades later.

Can it be fixed as an adult? Usually, yes. The canines can be reshaped with porcelain veneers or crowns so they look like lateral incisors, the front teeth can be lengthened, and the bite can be adjusted, often after a short course of clear aligners. For some adults, reopening the spaces for implants is the better route. Which one depends on your teeth, gums and bite, not on your age.

What is canine substitution?

The lateral incisors are the two smaller teeth on either side of your front teeth. About 1 to 2 percent of people are born without one or both. Canine substitution is one way orthodontists have managed that for decades: instead of holding the spaces open for replacement teeth, they move the canines forward into the lateral positions and let the teeth behind them follow.

It was, and often still is, a reasonable choice. Implants can’t be placed until growth is finished, and closing the space avoids replacement teeth entirely. The trade-off is that every tooth from the canine back now does a job it wasn’t shaped for. Those trade-offs show slowly.

Why do my teeth look different years after braces?

This is what I look for in an adult whose canines were moved forward:

  • Bulky teeth beside the front teeth. Canines are wider, thicker and more pointed than laterals. In a lateral’s position they make the front of the smile look crowded and heavy.
  • Front teeth that look short. Next to oversized neighbors, the two central incisors lose their dominance. Add decades of wear and the edges flatten, and the lower teeth start doing most of the showing.
  • Mismatched shade. Older restorations and natural teeth age differently, so the front of the smile ends up several colors at once.
  • A premolar at the corner of the smile. The tooth behind the canine moves into the canine’s place. It is narrower, and its inner point can show and catch as the jaw moves.
  • No canine guiding the bite. When the jaw slides sideways, the canines normally take the load. Moved forward, they can’t, and that job falls to teeth not built for it.
  • A narrow side. Closing space can leave one side of the upper arch sitting inside the lower teeth, with dark corners at the edge of the smile.

None of these can be fixed by veneering the front teeth in isolation. Which ones are present decides the plan.

The case

Look at the before photo above. The two front teeth are short and darker than the teeth on either side of them, with staining along their edges and a dark gap at the gumline between them. The teeth beside them are wide and rounded, sitting where laterals should be. The lower front teeth show more than the upper front teeth do. On one side, the back teeth step inward and the corner of the smile goes dark.

The goal was to correct what substitution left behind, match the dentistry she already had, and leave everything else alone. Her older restorations and her lower teeth were not part of this phase.

Aligners first. Clear aligner treatment moved the teeth toward a better bite and improved the narrow side before any restoration was made. The aligners did the tooth movement. Restorations can change how a tooth looks; they can’t move it.

Gums before teeth. Gum recontouring set each upper front tooth at the right height, and the small fold of tissue between the two front teeth was released. A veneer placed against the wrong gum line looks wrong however well it is made.

Veneers and crowns to finish. Porcelain veneers reshaped the canines to read as lateral incisors and lengthened the front teeth so their edges follow the lower lip. On the narrow side, crowns were contoured slightly fuller toward the cheek to improve the appearance of that side and fill the dark corner. The shade was matched to her existing work so old and new read as one smile.

The bite. With the canines no longer in the canine position, the new bite shares side-to-side chewing forces across several back teeth instead of relying on one, an arrangement called group function. The inner points of the premolars were adjusted so they don’t catch as the jaw moves.

In the after photo, the front teeth are longer and lead the smile again, the teeth beside them are narrower, the shade is one color, and the upper teeth now cover more of the lower teeth. The narrow side is better, not perfect. Her older restorations there were left as they were.

Had braces close gaps from missing teeth? Send photos through the free Virtual Smile Consultation and I’ll tell you what I’d look at first.

Should I reshape my canines or get implants?

For an adult, switching to implants usually means orthodontics to reopen both spaces, then two implants, each with its own bone and gum requirements, and a longer timeline. For some people that is the right answer, particularly when the canines are very large or the bone and gums are favorable. For many, reshaping and restoring the teeth already in position is the more conservative route. The evaluation decides which, not a preference for one treatment.

Is it too late to fix this as an adult?

Rarely. Age on its own is almost never the deciding factor. What decides it is the health of your gums and bone, the condition of your existing dental work, and how your bite functions. Older crowns and fillings don’t all have to be replaced at once either. A case can be phased, with new work matched to old, and older restorations replaced when they actually need it. That is how this case was done.

What does the evaluation involve?

I don’t plan a substitution case from a smile photo. I check how the teeth meet and guide in every direction, measure tooth proportions and gum heights, assess the bone and the existing restorations, and take full records. Then I plan the finished smile first, usually as a diagnostic wax-up, and work backward from it. That tells me which teeth need aligners, which need restoration, and which should be left alone.

Is canine substitution behind your smile? Signs to look for

Read this as a prompt to be evaluated, not a diagnosis:

  • You were told you were born missing teeth, or that your braces “closed spaces”
  • The teeth beside your front teeth look pointed, wide or bulky, or someone has called them vampire teeth
  • Your front teeth look short next to their neighbors
  • More of your lower teeth show than your upper teeth when you smile
  • The front of your smile is several different shades
  • A pointed tooth shows at the corner of your smile
  • Your smile looks narrow, with dark spaces at the corners
  • The gumline steps unevenly across your front teeth
  • Whitening changed the color and nothing about the shape

Two or three together is a pattern, not a coincidence.

Honest limits

Not every substitution case is a candidate for what is described here.

Restorations change shape and appearance. They do not correct a skeletal problem. A significant crossbite or jaw discrepancy needs orthodontic or surgical correction, and where that is the case I will refer rather than build porcelain to disguise it.

Gum disease, decay and other active problems are treated first. Cosmetic work placed over unresolved disease is a temporary result at a permanent price.

Group function is a compromise, not a return to normal. It spreads load sensibly, but if you clench or grind, protection, usually a night guard, is part of the plan rather than an add-on.

Veneers and crowns need maintenance and eventual replacement. Aligner results depend on wearing retainers.

Individual results vary. This case reflects one patient’s teeth, bite and existing dentistry, and it is not a prediction of anyone else’s outcome.

Questions patients ask

Am I too old for clear aligners?

Usually not. Gum and bone health matter more than age.

Can I get veneers if I had braces years ago?

Often, yes. But veneers are only as good as the tooth position, gumline and bite underneath them. If teeth have shifted since braces, alignment may need to come first, as in this smile makeover case.

Start with what’s actually there

I’m Dr. Rajvinder Dulay. I’ve practiced cosmetic dentistry in Tamarac for more than 20 years, and substitution cases are among the ones I find most worth doing carefully, because the right plan is different for every one of them. The first step is finding out which of the changes above you actually have.

Smile Makeover in Tamarac: What It Actually Takes to Rebuild a Worn Smile

Smile makeover before and after at a Tamarac cosmetic dentist: worn upper front teeth showing only a narrow band of tooth with the lower teeth dominating, then a restored smile with full upper incisors and a corrected smile line.


Smile makeover before and after. Actual patient of Dr. Dulay & Associates in Tamarac, published with consent. Individual results vary.

Look at the upper photo and count how much upper tooth you can actually see. A narrow strip. The lower teeth are doing most of the work in that smile, and they are not supposed to be.

Most people who come to me about a smile makeover arrive with a version of that complaint. The smile looks tired. The top teeth look short and flat — shorter than they used to be, and short enough that in photographs the upper teeth barely register while the bottom ones show more than they should. The edge of the smile runs straight across instead of curving. Whitening didn’t fix it. It made the teeth brighter and just as short.

And so the question I get asked is almost always the same one: how many veneers do I need?

That is the wrong first question, and answering it directly is how cosmetic cases fail.

A smile makeover is a sequence, not a product

“Veneers” is a material. A smile makeover is a plan — a specific order of steps that ends in veneers, where each step exists because the one after it will not work without it.

The reason this matters commercially, not just clinically: veneers bonded onto teeth in the wrong position, at the wrong shade, against the wrong gum line, in a bite that is still destructive, produce exactly the result everyone is afraid of. Bulky. Too white. Too flat. Chipped within a few years. That outcome is almost never the fault of the porcelain. It is the fault of the sequence, or the absence of one.

The case above is a good illustration, because on the surface it looked like a veneer case and underneath it was not one yet.

What was actually wrong

Retracted before and after view of a smile makeover: upper and lower front teeth meeting edge to edge with flat, translucent worn incisal edges and an uneven gum line, then restored tooth length, normal overlap and an even gingival contour.
Retracted view. Flat, translucent incisal edges and an edge-to-edge relationship — the cause of the wear, photographed. Actual patient, published with consent.

That retracted photograph is the diagnosis, and it is worth reading closely. The upper and lower front teeth meet tip to tip. There is essentially no vertical overlap. The upper incisal edges are flat and straight across, and grey and glassy where the enamel has thinned enough for the dentin underneath to show through. The lower incisors are worn in exactly the same way, because wear is a two-sided event. The gum line is uneven, sitting at different heights on teeth that should be symmetrical.

Three problems, stacked:

An edge-to-edge bite. Front teeth are built to shear past each other, not to hammer into each other. Meeting edge to edge, they grind themselves flat — a little more every year, and faster as they get shorter, because a shorter tooth meets its opponent harder.

A flattened smile line. A smile that reads as young follows the curve of the lower lip: longest at the two central incisors, sweeping up toward the corners. Because the centrals take the brunt of edge-to-edge contact, they wear fastest. The curve flattens, then eventually inverts into what is often called a reverse smile line. This case had not fully inverted yet. It was flat, which is the step before.

Lost lip support. The upper front teeth hold the upper lip out. Take length and thickness off them and the lip has less to rest against — it settles in, covers more of what is left, and the amount of tooth visible in conversation shrinks further.

Placing four veneers on that, and nothing else, would have looked better for a while and then broken. The bite that flattened natural enamel finds porcelain too. Porcelain is harder than enamel; it is not smarter than it.

The sequence I used

1. Orthodontic alignment first.
Before anything cosmetic, the front teeth had to be moved into a position where the uppers could overlap the lowers again, and where I would have room to add length back without immediately crashing into the opposing teeth. This is also the step that keeps a case conservative: teeth in the right position need less reduction than teeth being disguised in the wrong one. Short-course clear aligner treatment ahead of veneers is one of the most underused moves in cosmetic dentistry, and a limited case aimed at one specific problem is a very different proposition from the full-arch orthodontics most people picture.

2. Whitening.
Always before restorative work, never after — porcelain and composite do not respond to bleach. Whitening sets the shade that everything else is then matched to, so the natural teeth and the new work stay in agreement instead of drifting apart.

3. Gum recontouring.
Wear had shortened the teeth from the bottom while the gum line stayed where it was, leaving teeth that were both short and disproportionate, with zeniths at uneven heights. Recontouring re-established those high points so that length added at the edge produced a correctly proportioned tooth instead of a long one. Skipping this is why some veneer cases look like teeth that are simply too big.

4. Four porcelain veneers, finished with composite veneers.
Porcelain where the demand for strength, translucency and long-term stability was highest. Direct composite on the supporting teeth, blended into the porcelain. Mixing materials is a deliberate choice, not a budget compromise: it puts the strongest material exactly where the load is and keeps the rest of the case more conservative and more repairable.

Oblique smile makeover before and after showing improved upper lip support, a fuller arch through the corner of the smile, and increased upper tooth display after porcelain veneers.
Oblique view. Restoring length changes what the upper lip rests on — which changes how much tooth shows at rest and in speech. Actual patient, published with consent.

The oblique view shows the part most before-and-afters miss. The change is not just whiter teeth. It is upper tooth display — how much smile there is when the person is simply talking — and it is the fullness through the corner of the arch, where the before photo goes dark and the after does not. That comes from restored length and corrected position, and it is the difference between a result that looks like dentistry and a result that looks like a face.

Wondering whether your case is veneers alone or something more involved? Get in touch and I’ll tell you which one I think it is, at no charge.

Why some veneers look fake — and how the sequence prevents it

Nearly every “obvious veneer” result traces back to a step that was skipped:

  • Skipped alignment → teeth had to be over-prepared or over-built to fake a position, so they come out bulky and flat across the front
  • Skipped whitening → new restorations matched to dark natural teeth, or bright restorations sitting next to dark ones
  • Skipped gum work → correct-length teeth that read as square and oversized because the gum line never moved
  • No bite analysis → a flat, uniform edge with no individual character, built to survive rather than built to look right
  • One shade, no translucency → the single most recognizable tell, and purely a laboratory-communication problem

None of those are porcelain’s fault. You can see more finished cases in the smile gallery, and the porcelain veneers page covers materials and longevity in more detail.

What the evaluation involves

I do not plan a smile makeover from a selfie, and neither should anyone else. A real workup means measuring how much tooth structure has been lost against what should be there, checking how the teeth meet in centric and in excursions, reading the wear facets to determine whether the pattern comes from function, from clenching and grinding, or from acid erosion, evaluating the muscles and joints, taking full photographic records, and simulating the intended result before a single tooth is touched. That simulation is what tells me whether the length I want to add will survive the bite the patient actually has — and whether alignment, or in some cases a full mouth rehabilitation, needs to come first. A case planned backwards from the finished smile is a case that gets built once.

Is a smile makeover the right conversation for you?

Read this as a prompt to be evaluated, not a diagnosis:

  • Your upper front teeth look shorter than they do in older photographs
  • The bottom edges are flat and straight rather than gently curved
  • The edges look grey, glassy or translucent in bright light
  • Your top and bottom front teeth meet tip to tip when you bite together
  • Very little upper tooth shows when you talk; more lower tooth shows than you would expect
  • The middle of your smile sits level with, or lower than, the corners
  • Whitening helped the color and changed nothing about the shape
  • You have been quoted “just veneers” somewhere and it did not sit right with you
  • You have chipped a front tooth on something unremarkable
  • You catch yourself smiling with your lips closed in photographs

Two or three together is a pattern, not a coincidence.

Honest limits

Not every worn smile is a candidate for what is described here.

Alignment first adds months to the front end of a case. Some people do not want that. The honest answer is that skipping it means accepting either a more aggressive preparation or a result more likely to fail — and I would rather say that at the consultation than after the porcelain is bonded.

Severe wear that has closed the bite significantly is a larger problem than this case. It generally means rebuilding both arches rather than veneering the front six, and it belongs in the full mouth rehabilitation conversation.

Active gum disease, untreated decay, or a tooth needing root canal or surgical care is handled before any cosmetic work. Cosmetic dentistry placed over unresolved disease is a temporary result at a permanent price. Where a case genuinely requires oral surgery, orthognathic correction, or specialist care, restorative dentistry is not a substitute and I will refer.

Grinding and clenching do not stop because the teeth were restored. Protection — usually a night guard — is part of the plan, not an upsell after it.

Individual results vary. The result shown reflects one patient’s anatomy, bite and healing. It is not a prediction of any other outcome, and not every case is a candidate.

Start with a diagnosis, not a quote

If your front teeth are getting shorter, the window for a conservative result is closing a little every year. There was enough tooth left in this case to work with. That is not true forever.

Find out which category you are in — cosmetic or structural — before you spend money on the wrong one. I am a fee-for-service cosmetic dentistry practice in Tamarac and I have been doing this work in Broward County since 2004. The first conversation costs nothing.

Accessibility Toolbar