Can My Teeth Be Saved? How I Decide Between Saving and Removing a Tooth

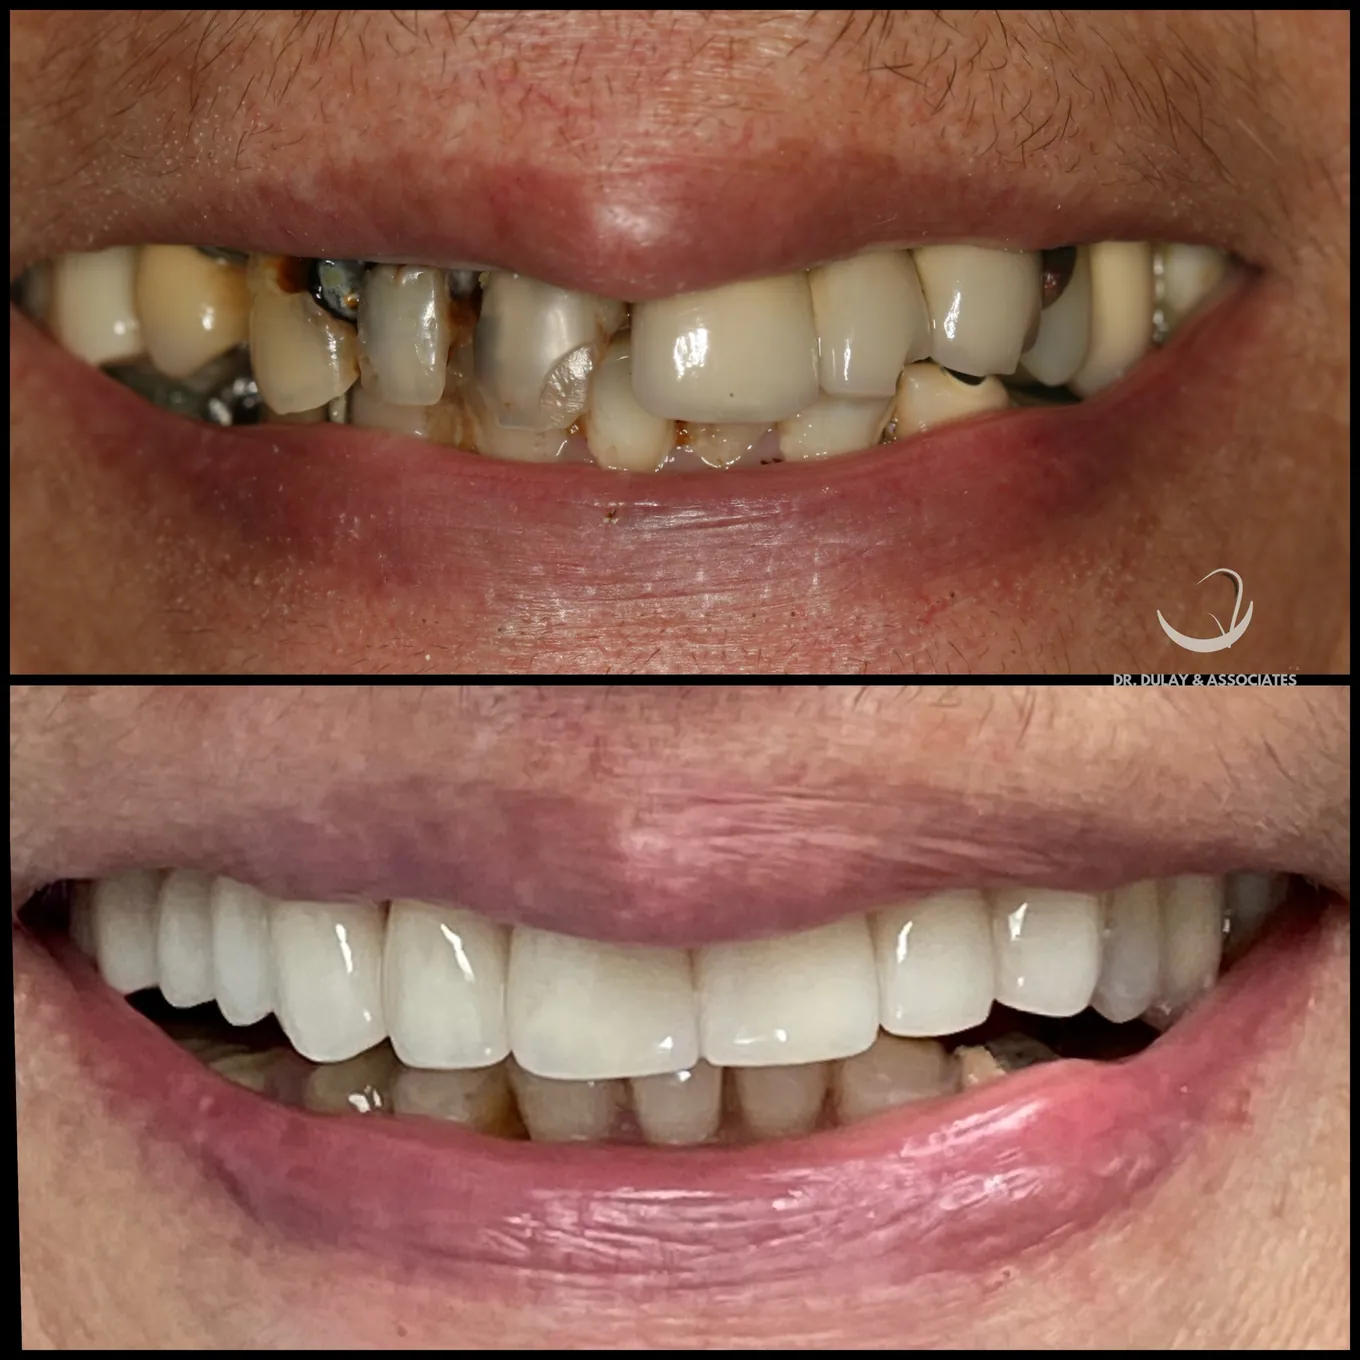
Before and after: broken, decayed upper teeth restored, every tooth kept by Dr. Rajvinder Dulay- Tamarac FL.

Maybe you’ve been told a tooth has to come out. Maybe you’ve looked at a mouth full of broken, dark, patched teeth and assumed the only answer left is dentures or implants. Either way, removing a tooth is the one dental decision that can’t be undone.

The short answer: often, yes. A tooth can usually be saved when three things are true: enough healthy tooth is left after the decay is removed to seal a restoration to, the root and the bone around it are sound, and any nerve problem can be treated with a root canal.

It usually can’t be saved when the root is cracked, the decay runs below the bone, or the bone support is gone.

What a tooth looks like tells you surprisingly little. Some teeth that look hopeless have strong roots and plenty of sound structure underneath. Some that look fine are cracked to the root. The decision is made below the surface: on X-rays, and once the decay is out.

What decides whether a tooth can be saved

1. How much healthy tooth is left

Decay is removed first. What matters is what remains: enough sound tooth, especially at the edges near the gum, for a new restoration to seal against. If the edges can be sealed, decay has nowhere to get back in. If they can’t, a restoration will fail no matter how well it’s made.

2. The nerve

When decay reaches the nerve, the nerve becomes inflamed or infected. That isn’t a reason to remove the tooth. A root canal cleans out the inside of the tooth and seals it. I do most of my root canals myself and refer the complex ones to an endodontist. A tooth that has had a root canal then needs a restoration that protects it.

3. The root and the bone

A strong root in healthy bone is what makes a tooth worth rebuilding. A root that’s cracked lengthwise can’t be repaired. Severe bone loss from gum disease can leave a tooth too loose to support anything. These are the two most common reasons a tooth truly has to go.

4. The rest of your mouth, and what you want

One tooth is never decided alone. How it fits in your bite, what the teeth around it need, and what you want, including whether you want to avoid surgery, all shape the plan.

Why saving a tooth is worth the effort

An implant is a good replacement. It is still a replacement. Removing a tooth and placing an implant means surgery, healing time and more steps. A natural tooth keeps its own root and the ligament that cushions it in the bone.

Saving a tooth also means choosing how to rebuild it. Where I can, I use an inlay or onlay, which replaces only what’s missing, instead of a crown, which needs the whole tooth shaped down. Keeping more of the tooth is the point.

Teeth that were saved, from least to most damaged

Every tooth below was a candidate for extraction by appearance alone. Each was kept.

A small spot over deep decay

Biting surface of a lower molar with one small dark spot in the groove.Before
The same molar restored with a tooth-colored ceramic restoration.Saved
From the surface, one small dark spot. Underneath, the decay had reached the nerve. Saved with a root canal and a ceramic restoration. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

Decay close to the nerve

Upper molar with a cavity broken open between the teeth, exposing dark decay.Before
The same molar after a root canal and a ceramic restoration.Saved
The cavity had worked in from between the teeth until it sat against the nerve. Saved with a root canal and a ceramic restoration. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

Decay hiding under an old silver filling

Lower molar with a large old silver filling that looks intact.Before
The same molar after the old filling and decay were removed and the tooth was rebuilt in ceramic.Saved
The old filling looked intact. Underneath it, decay had spread through the tooth. The filling and decay were removed and the tooth rebuilt in ceramic. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

Half the tooth broken away

Upper molar with a large part of the side broken away and brown decay exposed.Before
The same molar restored with a ceramic onlay.Saved
A large part of the tooth had broken off around decay. After a root canal, it was rebuilt with an onlay rather than a crown, which kept more of the natural tooth. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

Decayed down to the gumline

Lower molar with decay that has broken away the back of the tooth down to the gum.Before
The same molar after a root canal and restoration.Saved
Decay had destroyed the back wall of this tooth down to the gum. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.
Upper molar with most of its biting surface destroyed by decay.Before
The same molar restored after a root canal.Saved
Most of the biting surface was gone. In both teeth, the roots and bone were sound and the edges could be sealed, so both were saved with a root canal and restoration. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

Save it, or take it out and place an implant?

Lower molar after decay removal, with the inside of the tooth rebuilt and sound walls remaining.Before
The same molar restored with a ceramic inlay.Saved
The tooth after the decay was removed, and the finished e.max ceramic inlay. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.
X-ray of the saved molar after its root canal, with an implant replacing the missing tooth beside it.X-ray
The finished root canal, with the implant that replaced the patient’s missing tooth next to it.

This patient had already lost the tooth next to this one, and it had been replaced with an implant. When this tooth needed treatment, extraction and a second implant was an option. The patient didn’t want another surgery and didn’t want to lose another natural tooth.

After the decay was removed, enough healthy tooth was left to seal the edges of a ceramic inlay, and the roots and bone were strong. So I saved it: a root canal, then an e.max inlay.

A whole upper arch, every tooth kept

Smile showing broken upper teeth, failing old crowns and dark decay at the gumline.Before
The same smile with every upper tooth restored.After
Broken teeth, failing old crowns and decay across the upper teeth. Every tooth was kept and restored. The lower teeth are the patient's own healthy natural teeth and didn't need treatment. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.
Upper teeth seen from below, with dark failing fillings, old silver fillings and decay.Before
The same upper teeth after every tooth was restored with tooth-colored work.After
A different patient: failing old fillings and decay across the upper teeth. Every tooth was kept and restored. Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

When this many teeth are involved, fixing them one at a time as each one fails is the least predictable way to do it. I plan the whole mouth first, often working out the bite on models before I touch a tooth, then rebuild in a sensible order.

Been told a tooth has to come out, or wondering whether your teeth can be saved? Send photos through the free Virtual Smile Consultation and I’ll tell you whether it’s worth coming in.

How I evaluate a tooth before deciding

I don’t decide whether a tooth can be saved from a photo. I examine it, take X-rays that show the whole root and the bone around it, and test the nerve. I look for cracks and check the gum and bone support. If the tooth might be saved, the final answer often comes once the decay is removed and I can see what’s left. When several teeth are failing, I plan the whole mouth before treating any of them, so each repair fits with the next.

Questions to ask before a tooth is removed

Read this as a prompt for a conversation with your dentist, not a diagnosis:

  • Is the root cracked, or is the damage in the part of the tooth above the gum?
  • How much healthy tooth will be left once the decay is out?
  • Does it need a root canal, and is it a straightforward one?
  • How is the bone around it?
  • What would replacing it involve, compared with saving it?
  • Could it be rebuilt with an onlay instead of a crown?
  • If several teeth are failing, has anyone planned the whole mouth, or only the next tooth?

If nobody has answered these, a second opinion before an extraction is reasonable.

Don’t wait on these. Swelling in the gum or face, a pimple-like bump on the gum, fever, or tooth pain that wakes you up: call the office the same day, or see our emergency dental care page.

Swelling that spreads toward the eye or down the neck, or any difficulty swallowing or breathing, is a medical emergency. Go to the emergency room.

Honest limits

Not every tooth can be saved. A root cracked lengthwise, decay that runs below the bone, or a tooth with too little bone left are usually beyond saving, and keeping them only delays the inevitable. In those cases extraction is the right call.

Saving every tooth isn’t always the best plan for the mouth as a whole. Occasionally removing one tooth makes the rest of the plan work better.

A saved tooth still needs care. Teeth that have had a root canal need a protective restoration, and any tooth can develop new problems later.

Where a case needs an endodontist or an oral surgeon, I refer. Individual results vary, and not every tooth or case is a candidate for any particular treatment.

Questions patients ask

Is it better to save a tooth or get an implant?

When a tooth can be saved predictably, saving it usually means less surgery and keeps your natural root. When it can’t, an implant is a good replacement. The answer depends on the tooth, which is why it needs an exam and X-rays.

Can a tooth with a huge cavity be saved?

Often. The size of the cavity matters less than what’s left once the decay is removed, and whether the root and bone are healthy.

Can a tooth broken at the gumline be saved?

Sometimes. If enough sound tooth remains at or just below the gum to seal a restoration to, and the root is intact, it can often be rebuilt. If the break runs down the root, it usually can’t.

Find out before anything comes out

I’m Dr. Rajvinder Dulay. I’ve practiced restorative dentistry and full mouth rehabilitation in Tamarac for more than 20 years. Every tooth in this post could have been extracted. An extraction is permanent, so it’s worth finding out first whether it has to be.
Born Without Lateral Incisors? Fixing Canine Substitution Years After Braces

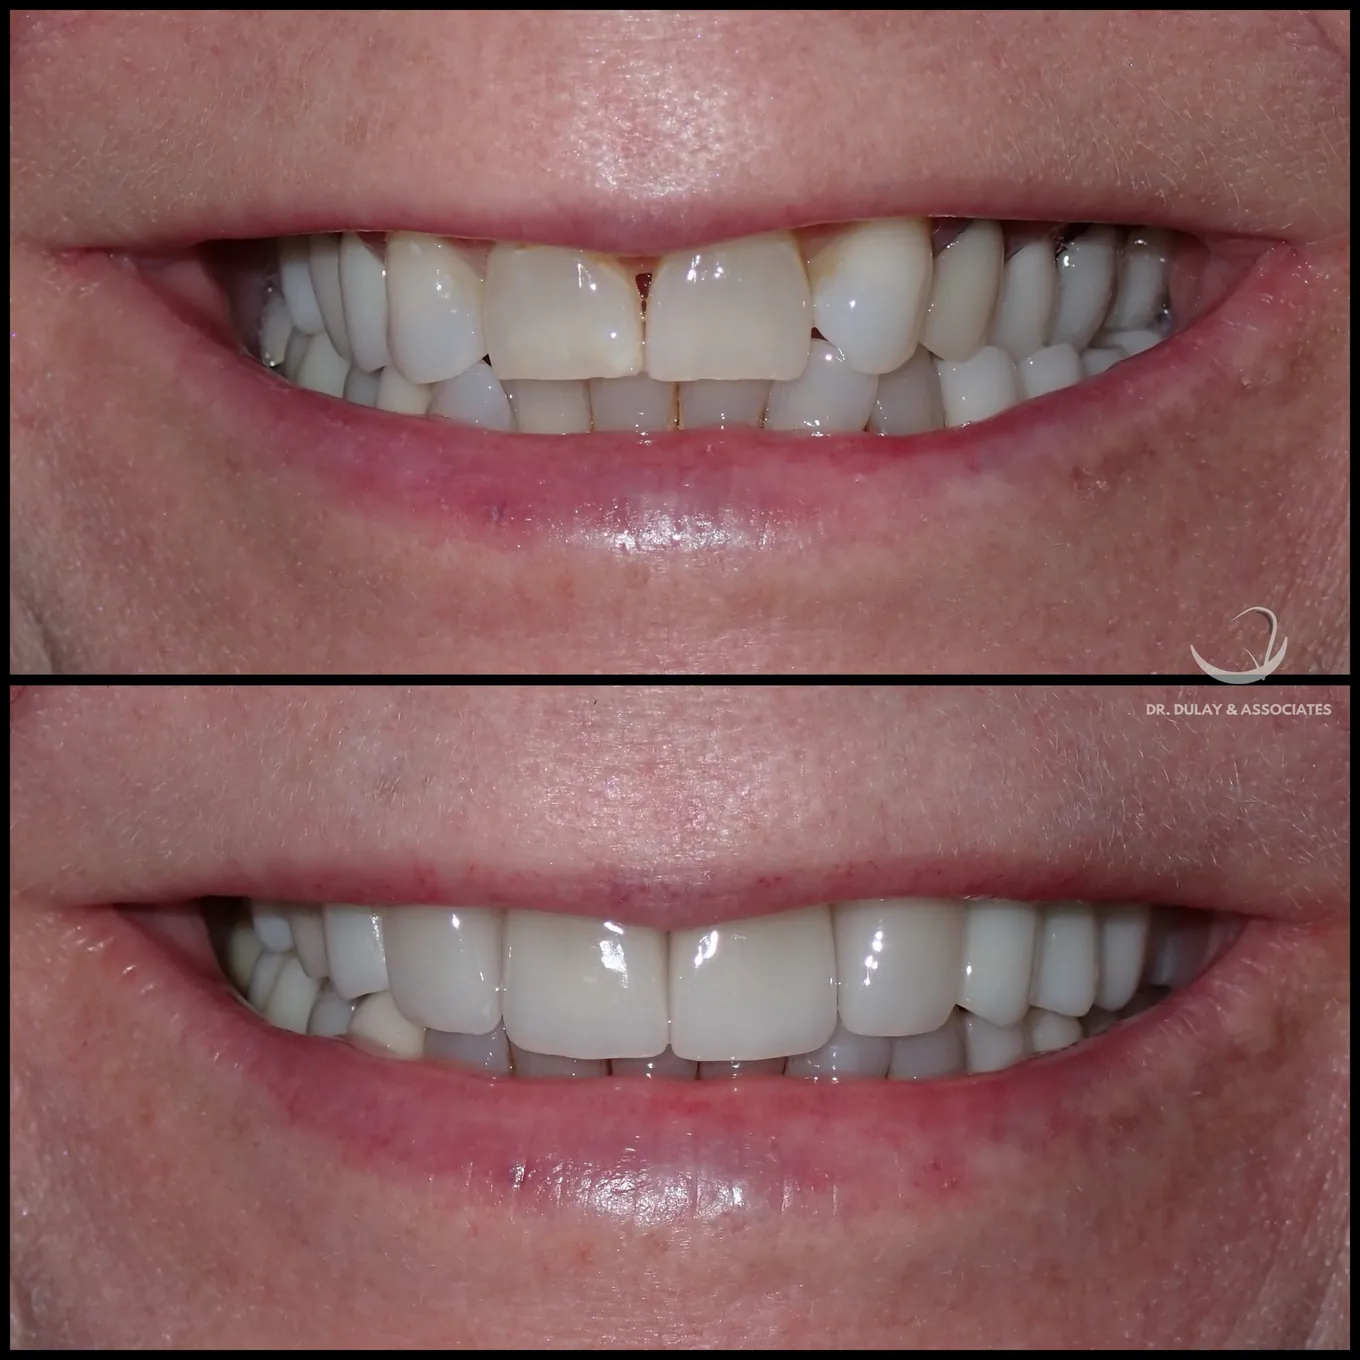
Before and after: short, stained front teeth with wide canines standing in for missing lateral incisors, then longer front teeth with the canines reshaped as laterals.

Above: before (top) and after (bottom). Actual patient of Dr. Dulay & Associates, published with consent. Individual results vary.

You had braces as a teenager. You were told you were born without two teeth, and the orthodontist closed the gaps. It worked, and for years you didn’t think about it. Now the teeth beside your front teeth look pointed, almost like vampire teeth, and too heavy for where they sit, your front teeth look short, and your smile looks narrower than it should.

That isn’t your imagination, and it isn’t just age. It is what canine substitution looks like decades later.

Can it be fixed as an adult? Usually, yes. The canines can be reshaped with porcelain veneers or crowns so they look like lateral incisors, the front teeth can be lengthened, and the bite can be adjusted, often after a short course of clear aligners. For some adults, reopening the spaces for implants is the better route. Which one depends on your teeth, gums and bite, not on your age.

What is canine substitution?

The lateral incisors are the two smaller teeth on either side of your front teeth. About 1 to 2 percent of people are born without one or both. Canine substitution is one way orthodontists have managed that for decades: instead of holding the spaces open for replacement teeth, they move the canines forward into the lateral positions and let the teeth behind them follow.

It was, and often still is, a reasonable choice. Implants can’t be placed until growth is finished, and closing the space avoids replacement teeth entirely. The trade-off is that every tooth from the canine back now does a job it wasn’t shaped for. Those trade-offs show slowly.

Why do my teeth look different years after braces?

This is what I look for in an adult whose canines were moved forward:

  • Bulky teeth beside the front teeth. Canines are wider, thicker and more pointed than laterals. In a lateral’s position they make the front of the smile look crowded and heavy.
  • Front teeth that look short. Next to oversized neighbors, the two central incisors lose their dominance. Add decades of wear and the edges flatten, and the lower teeth start doing most of the showing.
  • Mismatched shade. Older restorations and natural teeth age differently, so the front of the smile ends up several colors at once.
  • A premolar at the corner of the smile. The tooth behind the canine moves into the canine’s place. It is narrower, and its inner point can show and catch as the jaw moves.
  • No canine guiding the bite. When the jaw slides sideways, the canines normally take the load. Moved forward, they can’t, and that job falls to teeth not built for it.
  • A narrow side. Closing space can leave one side of the upper arch sitting inside the lower teeth, with dark corners at the edge of the smile.

None of these can be fixed by veneering the front teeth in isolation. Which ones are present decides the plan.

The case

Look at the before photo above. The two front teeth are short and darker than the teeth on either side of them, with staining along their edges and a dark gap at the gumline between them. The teeth beside them are wide and rounded, sitting where laterals should be. The lower front teeth show more than the upper front teeth do. On one side, the back teeth step inward and the corner of the smile goes dark.

The goal was to correct what substitution left behind, match the dentistry she already had, and leave everything else alone. Her older restorations and her lower teeth were not part of this phase.

Aligners first. Clear aligner treatment moved the teeth toward a better bite and improved the narrow side before any restoration was made. The aligners did the tooth movement. Restorations can change how a tooth looks; they can’t move it.

Gums before teeth. Gum recontouring set each upper front tooth at the right height, and the small fold of tissue between the two front teeth was released. A veneer placed against the wrong gum line looks wrong however well it is made.

Veneers and crowns to finish. Porcelain veneers reshaped the canines to read as lateral incisors and lengthened the front teeth so their edges follow the lower lip. On the narrow side, crowns were contoured slightly fuller toward the cheek to improve the appearance of that side and fill the dark corner. The shade was matched to her existing work so old and new read as one smile.

The bite. With the canines no longer in the canine position, the new bite shares side-to-side chewing forces across several back teeth instead of relying on one, an arrangement called group function. The inner points of the premolars were adjusted so they don’t catch as the jaw moves.

In the after photo, the front teeth are longer and lead the smile again, the teeth beside them are narrower, the shade is one color, and the upper teeth now cover more of the lower teeth. The narrow side is better, not perfect. Her older restorations there were left as they were.

Had braces close gaps from missing teeth? Send photos through the free Virtual Smile Consultation and I’ll tell you what I’d look at first.

Should I reshape my canines or get implants?

For an adult, switching to implants usually means orthodontics to reopen both spaces, then two implants, each with its own bone and gum requirements, and a longer timeline. For some people that is the right answer, particularly when the canines are very large or the bone and gums are favorable. For many, reshaping and restoring the teeth already in position is the more conservative route. The evaluation decides which, not a preference for one treatment.

Is it too late to fix this as an adult?

Rarely. Age on its own is almost never the deciding factor. What decides it is the health of your gums and bone, the condition of your existing dental work, and how your bite functions. Older crowns and fillings don’t all have to be replaced at once either. A case can be phased, with new work matched to old, and older restorations replaced when they actually need it. That is how this case was done.

What does the evaluation involve?

I don’t plan a substitution case from a smile photo. I check how the teeth meet and guide in every direction, measure tooth proportions and gum heights, assess the bone and the existing restorations, and take full records. Then I plan the finished smile first, usually as a diagnostic wax-up, and work backward from it. That tells me which teeth need aligners, which need restoration, and which should be left alone.

Is canine substitution behind your smile? Signs to look for

Read this as a prompt to be evaluated, not a diagnosis:

  • You were told you were born missing teeth, or that your braces “closed spaces”
  • The teeth beside your front teeth look pointed, wide or bulky, or someone has called them vampire teeth
  • Your front teeth look short next to their neighbors
  • More of your lower teeth show than your upper teeth when you smile
  • The front of your smile is several different shades
  • A pointed tooth shows at the corner of your smile
  • Your smile looks narrow, with dark spaces at the corners
  • The gumline steps unevenly across your front teeth
  • Whitening changed the color and nothing about the shape

Two or three together is a pattern, not a coincidence.

Honest limits

Not every substitution case is a candidate for what is described here.

Restorations change shape and appearance. They do not correct a skeletal problem. A significant crossbite or jaw discrepancy needs orthodontic or surgical correction, and where that is the case I will refer rather than build porcelain to disguise it.

Gum disease, decay and other active problems are treated first. Cosmetic work placed over unresolved disease is a temporary result at a permanent price.

Group function is a compromise, not a return to normal. It spreads load sensibly, but if you clench or grind, protection, usually a night guard, is part of the plan rather than an add-on.

Veneers and crowns need maintenance and eventual replacement. Aligner results depend on wearing retainers.

Individual results vary. This case reflects one patient’s teeth, bite and existing dentistry, and it is not a prediction of anyone else’s outcome.

Questions patients ask

Am I too old for clear aligners?

Usually not. Gum and bone health matter more than age.

Can I get veneers if I had braces years ago?

Often, yes. But veneers are only as good as the tooth position, gumline and bite underneath them. If teeth have shifted since braces, alignment may need to come first, as in this smile makeover case.

Start with what’s actually there

I’m Dr. Rajvinder Dulay. I’ve practiced cosmetic dentistry in Tamarac for more than 20 years, and substitution cases are among the ones I find most worth doing carefully, because the right plan is different for every one of them. The first step is finding out which of the changes above you actually have.

Accessibility Toolbar